Spinal Pain Management Guide: Treatment Strategies, Therapy Options, Specialist Care, and Recovery Planning
Spinal pain can involve the neck, upper back, mid-back, or lower back and may result from muscles, joints, discs, nerves, or other structures around the spine.
The appropriate treatment depends on the underlying cause, symptom pattern, duration, severity, neurological findings, medical history, and individual circumstances. Some spinal pain improves with conservative care, while persistent or complicated symptoms may require specialist evaluation.
Spinal pain should therefore be approached as a broad category rather than a single condition.
Common Causes of Spinal Pain
Potential causes of spinal pain include:
Muscle or ligament strain
Degenerative spinal changes
Herniated or bulging discs
Spinal stenosis
Arthritis affecting spinal joints
Nerve irritation or compression
Vertebral fractures
Certain inflammatory conditions
Previous injuries
Less-common structural or systemic conditions
Pain location alone does not always identify its cause. A healthcare professional may use the symptom pattern, examination findings, medical history, and appropriate testing to determine the likely source.
Types of Spinal Pain
Spinal pain may be described according to location or characteristics.
Neck pain
Cervical spine problems can cause pain and stiffness in the neck and may sometimes produce symptoms extending into the shoulder, arm, or hand.
Upper and mid-back pain
Thoracic spinal pain can involve the area between the neck and lower back. Causes may include muscular strain, posture-related problems, joint conditions, or other spinal disorders.
Lower-back pain
Lumbar pain is common and may arise from muscles, discs, joints, nerves, or other structures.
Radiating pain
Pain that travels into an arm or leg may indicate nerve irritation or compression and can require a different evaluation from uncomplicated localized back pain.
How Spinal Pain Is Evaluated
A medical evaluation may include:
Symptom history
Pain location and duration
Physical examination
Muscle-strength testing
Reflex assessment
Sensory testing
Range-of-motion assessment
Review of previous injuries
Medication review
Assessment of functional limitations
Imaging is not necessarily required for every episode of spinal pain. X-rays, MRI, CT, or other tests may be considered when specific findings or persistent symptoms indicate that additional investigation could be useful.
Conservative Treatment Approaches
Many spinal-pain conditions are initially managed with conservative approaches.
Depending on the diagnosis, these may include:
Maintaining appropriate physical activity
Activity modification
Physical therapy
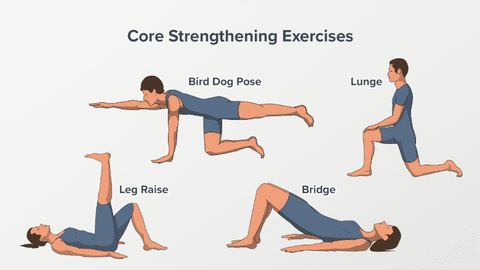
Strengthening exercises
Mobility exercises
Education about movement and posture
Weight management when appropriate
Heat or cold for temporary symptom relief
Medication when clinically appropriate
Treatment should be adjusted if symptoms worsen or new neurological findings appear.
Physical Therapy
Physical therapy can be an important component of spinal-pain management.
A physical therapist may develop a program focused on:
Spinal mobility
Core strengthening
Postural control
Hip and lower-body strength
Flexibility
Balance
Movement mechanics
Functional activity
Gradual return to normal activities
The appropriate exercises depend on the cause of pain. An exercise that is appropriate for one spinal condition may not be appropriate for another.
Activity and Recovery Planning
Avoiding all movement for prolonged periods is not appropriate for many uncomplicated spinal-pain conditions.
A gradual recovery plan may involve:
Identifying activities that aggravate symptoms
Modifying those activities temporarily
Maintaining tolerable movement
Gradually increasing physical activity
Rebuilding strength and mobility
Returning progressively to normal activities
Recovery should be individualized rather than based on a fixed timeline.
Medication Options
Medication may sometimes help manage spinal pain, depending on the diagnosis and individual health factors.
Potential categories include:
Nonsteroidal anti-inflammatory drugs (NSAIDs)
Acetaminophen in selected situations
Prescription medicines when clinically appropriate
Medications targeting specific nerve-related symptoms
NSAIDs can have gastrointestinal, kidney, cardiovascular, and medication-interaction risks. A healthcare professional or pharmacist can help determine whether a particular medication is appropriate.
Prescription medications should not be started, stopped, or changed without appropriate clinical guidance.
Specialist Care
Persistent or complicated spinal pain may require evaluation by a specialist.
Depending on the symptoms, healthcare professionals involved may include:
Primary-care clinicians
Physical therapists
Physiatrists
Orthopedic specialists
Neurosurgeons
Neurologists
Rheumatologists
Pain-management specialists
The appropriate specialist depends on the suspected cause and whether neurological, structural, inflammatory, or functional issues are present.
When Imaging May Be Considered
Imaging decisions depend on the clinical situation.
Imaging may be considered when there are:
Persistent symptoms despite appropriate conservative care
Significant neurological findings
Suspected fracture
History or findings suggesting infection
Concern about serious underlying disease
Symptoms that require planning for an intervention
MRI can provide detailed information about discs, nerves, the spinal cord, and other soft tissues. X-rays can provide information about bones and alignment, while CT can provide detailed bony imaging in selected circumstances.
Imaging should be interpreted in the context of symptoms and physical findings because abnormalities can sometimes occur without causing pain.
Injections and Interventional Treatment
Some spinal conditions may be treated with targeted procedures.
Depending on the diagnosis, clinicians may consider:
Epidural steroid injections
Facet-related injections
Nerve-targeted procedures
Other image-guided interventions
These treatments are not appropriate for every patient or every type of spinal pain. Potential benefits, risks, and alternatives should be discussed with an appropriately qualified clinician.
Surgical Evaluation
Surgery is generally considered when there is a specific structural problem for which surgery may provide meaningful benefit.
Possible reasons for surgical evaluation include:
Progressive neurological weakness
Significant nerve or spinal-cord compression
Certain spinal fractures
Structural instability
Persistent disabling symptoms despite appropriate conservative management
A condition with a recognized surgical treatment pathway
The decision depends on the diagnosis, symptoms, imaging findings, overall health, and expected benefits and risks.
Spinal Pain and Workplace Activities
Work-related activities can sometimes contribute to spinal symptoms.
Risk factors may include:
Repetitive lifting
Awkward postures
Prolonged sitting
Repetitive bending
Vibration exposure
Poorly adjusted workstations
Sudden increases in physical workload
Workplace modifications may include appropriate ergonomic adjustments, movement breaks, task modification, and safer lifting practices.
Sleep and Daily Activities
Spinal pain can affect sleep, mobility, work, and everyday activities.
A care plan may address:
Comfortable sleep positioning
Mattress and pillow considerations
Activity pacing
Workplace ergonomics
Safe movement
Gradual physical activity
Stress and fatigue management
These measures may support recovery but should not replace medical evaluation when symptoms are persistent or concerning.
Warning Signs Requiring Prompt Evaluation
Some spinal-pain symptoms can indicate a potentially serious condition.
Prompt medical evaluation may be appropriate for:
New or worsening muscle weakness
Significant numbness
Loss of coordination
Severe pain after major trauma
Fever associated with spinal pain
Unexplained weight loss with persistent pain
History of cancer with new spinal symptoms
Severe pain that is rapidly worsening
Emergency evaluation is particularly important when spinal pain occurs with new bladder or bowel dysfunction, numbness around the groin or inner thighs, or rapidly progressing weakness.
Recovery Planning
A practical spinal-pain recovery plan can include:
| Area | Planning Consideration |
|---|---|
| Diagnosis | What is the suspected source of pain? |
| Symptoms | Which movements or activities aggravate symptoms? |
| Activity | What movement is currently tolerable? |
| Therapy | Would physical therapy be appropriate? |
| Medication | Are medications appropriate given other health factors? |
| Work | Are ergonomic or activity changes needed? |
| Monitoring | Are strength, sensation, and function changing? |
| Follow-up | When should symptoms be reassessed? |
| Escalation | What warning signs require prompt evaluation? |
The plan can be adjusted as symptoms and function change.
Recent Developments in Spinal Pain Management
Modern spinal-pain care increasingly emphasizes individualized treatment and appropriate use of conservative management before invasive interventions when clinically appropriate.
There is also greater emphasis on physical activity, rehabilitation, patient education, and functional recovery rather than focusing solely on pain intensity.
For persistent symptoms, clinicians increasingly consider the interaction between physical findings, neurological symptoms, functional limitations, and the patient's broader health circumstances when determining the next treatment step.
Spinal Pain Management Checklist
Patients discussing spinal pain with a healthcare professional may consider:
Record when symptoms began
Identify the location of pain
Note whether pain radiates into an arm or leg
Record numbness or tingling
Monitor changes in strength
Identify activities that worsen symptoms
Review current medications
Discuss physical therapy
Determine whether imaging is appropriate
Discuss workplace or activity modifications
Establish recovery goals
Understand warning signs
Arrange follow-up when symptoms persist or change
Tools and Resources
Useful resources for learning about spinal pain include:
NIAMS: Educational information about musculoskeletal conditions.
NINDS: Information concerning neurological conditions affecting the nervous system.
MedlinePlus: General health information about back pain and related conditions.
Physical therapists: Individualized movement, strengthening, and rehabilitation guidance.
Physiatrists: Specialists focused on physical medicine and rehabilitation.
Orthopedic and spine specialists: Evaluation of structural spinal conditions.
Pain-management professionals: Assessment of persistent or complex pain.
Frequently Asked Questions
1. What is the best treatment for spinal pain?
There is no single treatment that is appropriate for everyone. Treatment depends on the cause, location, severity, duration, neurological findings, and individual health factors. Options may include physical therapy, activity modification, medication, specialist care, procedures, or surgery in selected situations.
2. Can physical therapy help spinal pain?
Physical therapy can help many people improve strength, mobility, movement patterns, and functional ability. The program should be tailored to the underlying condition and individual symptoms.
3. When should spinal pain be evaluated by a specialist?
Specialist evaluation may be appropriate when symptoms persist despite conservative care, significant neurological symptoms develop, imaging identifies a structural problem, or the underlying cause requires specialized treatment.
4. Is an MRI always needed for spinal pain?
No. Imaging is not necessary for every episode of spinal pain. The decision depends on symptoms, examination findings, duration, suspected cause, and whether the result would change management.
5. When is spinal pain an emergency?
New bladder or bowel dysfunction, numbness around the groin or inner thighs, rapidly progressing weakness, or severe symptoms after significant trauma can require urgent medical evaluation.
Conclusion
Spinal pain can have many different causes, so effective management begins with identifying the most likely source and understanding the individual's symptoms and functional limitations.
Physical therapy, appropriate activity, medication when indicated, specialist evaluation, workplace modifications, targeted procedures, and surgery can all have a role depending on the diagnosis.
A structured recovery plan can help connect symptom monitoring, rehabilitation, medical follow-up, and gradual return to normal activities.

Related Post...

Neuropathic Pain Management Guide: Treatment Options, Nerve Therapy, Medications, and Care Insights
Updated: October 07, 2026
Read More